C., Chen Y

Consider using CGM to assess glycaemic response to foods (especially if you were glucose dysregulated before) Expected outcomes: Appetite reduction, 25% waist circumference and weight loss, early visceral fat reduction, improved post-meal glucose responses Month 35: Acceleration Phase Reach therapeutic steady GLP-1 dose Use CGM data to guide food choices where necessary Resistance training becomes part of routine and needs to be progressive (ie once strength improves and it becomes easy, lift heavier weights) Waist circumference continues to drop, even if weight remains steady (as muscle weighs more than adipose tissue) Likely improvement in glycaemic and MASLD blood markers Expected outcomes: 510% total body weight loss, increased insulin sensitivity, improved energy levels, lowered blood pressure Month 68: Transition Phase Emphasis shifts to muscle preservation and metabolic independence Protein intake and strength training remain central For those reaching waist goals, begin tapering GLP-1 dose under supervision Expected outcomes: Stable lean mass, reduced visceral fat, better metabolic flexibility, readiness to stop medication How Do We Measure Success

Standard urine tests detect ethyl glucuronide (EtG), a byproduct of alcohol
Collectively they found that a truncated form of GLP-1 produced by gut cells was able to bind a G-protein coupled receptor (GPCR) expressed on pancreatic islet cells and in other tissues
Some critics argue that they can lead to side effects and long-term health risks, and that they may be used as a shortcut to achieving fitness goals
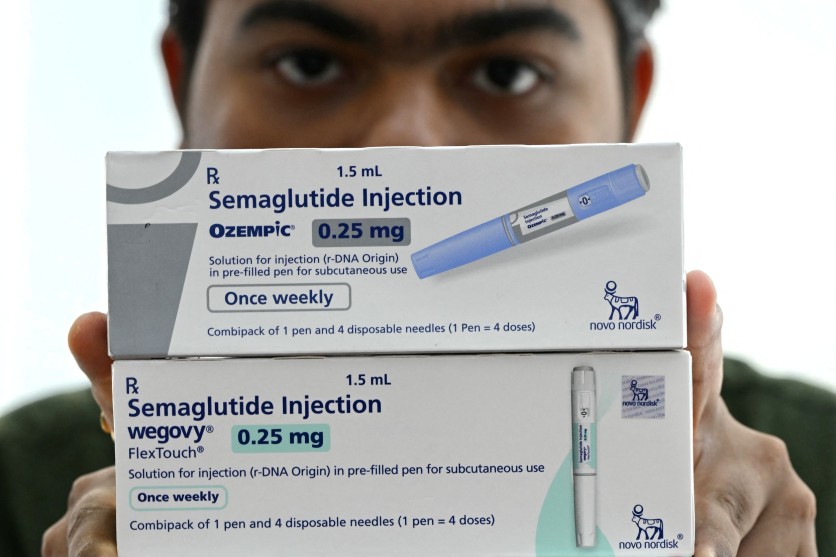
Patient Education: Patients who have been using compounded semaglutide should be informed about this change and the importance of accessing FDA-approved medications moving forward