Trn y l bi vit v glutathione c tc dng g vi da, l thnh phn lm trng da tuyt vi m nh thuc Long Chu gi n bn
doi: 10.1111/dom.12824 10 ZaazoueeMSHamdallahAHelmySKHasaboEASayedAKGbreelMIet al
The percent changes from baseline in BP reps and third set lifting volume were both 27.5% for the LCR group
Regular blood glucose monitoring becomes essential, and some patients may need adjustments to their semaglutide dose or prednisone timing to optimize control
Enhances Skin Brightness: Works to lighten the complexion and reduce the appearance of dark spots and uneven skin tone
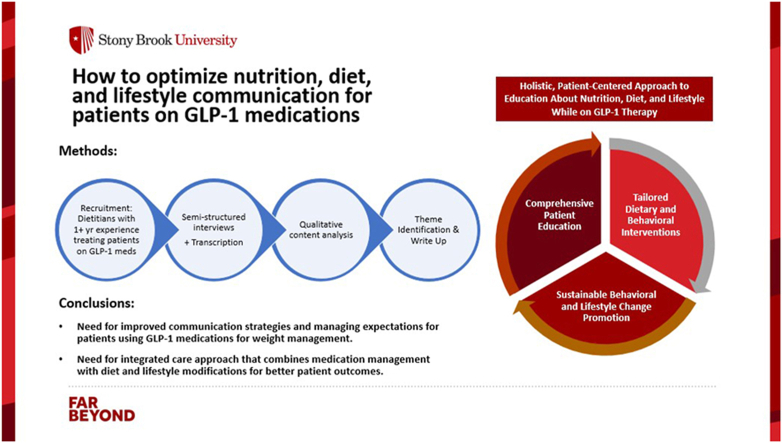
My Approach When Prescribing Here's my general framework not a rigid protocol, but a starting point for the conversation: I Tend to Start with Semaglutide When The patient has established cardiovascular disease (because of the SELECT trial data) Insurance covers semaglutide but not tirzepatide The patient has MASH/fatty liver disease Cost is the primary concern and semaglutide is more accessible I Tend to Start with Tirzepatide When Maximum weight loss is the primary goal The patient has type 2 diabetes (tirzepatide shows greater A1C reduction roughly 2.02.5% vs 1.02.0% for semaglutide) The patient has tried semaglutide with insufficient results Insurance covers both options equally Regardless of which medication we choose, I always emphasize that GLP-1 therapy is most effective when combined with nutritional counseling, physical activity, and behavioral support