Monitoring recommendations Researchers using cagrilintide should consider regular monitoring including: Blood work every 3 to 6 months including metabolic panel, lipid panel, liver function, and pancreatic enzymes Thyroid function tests at baseline and periodically Body composition assessment to track lean mass versus fat mass changes Heart rate monitoring particularly during titration Nutritional status markers including vitamin B12, iron, and vitamin D The peptide research and studies section provides broader context for evaluating emerging safety data as it becomes available
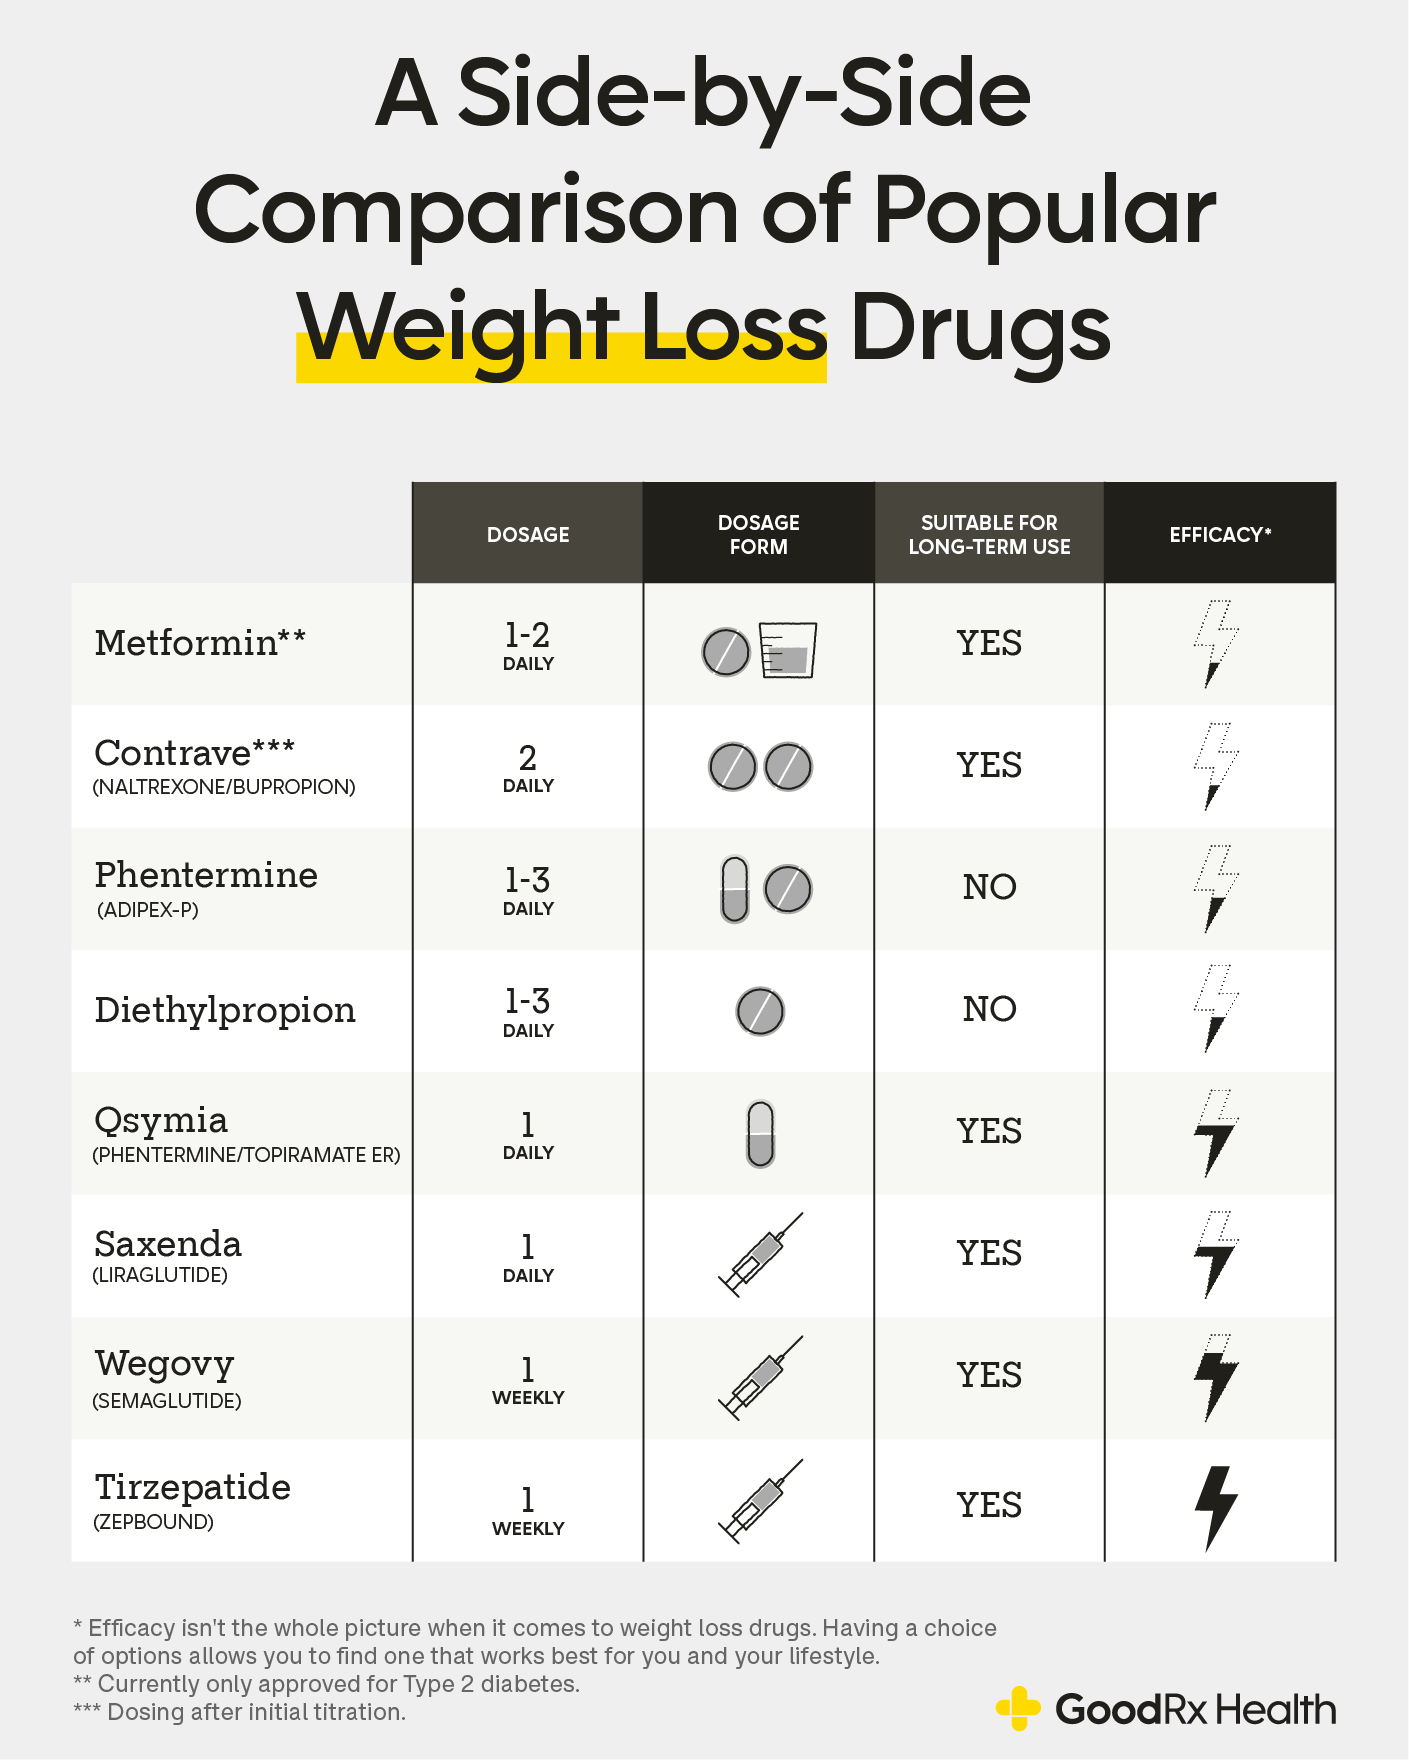
As a result of being peptides, GLP-1 RAs typically have to be given by subcutaneous (s.c.) administration as twice daily (BID) (exenatide) [15, 16], once daily (OD) (lixisenatide [17, 18] and liraglutide [19, 20]) or once weekly (OW) (dulaglutide [21, 22], prolonged-release exenatide [23, 24] and semaglutide [25, 26]) dosing regimens, based on their in vivo half-lives [6]
SGLT2 Inhibitors SGLT2 inhibitors, another class of medications used in the management of Type 2 diabetes, work by preventing the kidneys from reabsorbing glucose back into the bloodstream, leading to its excretion through urine
AAV2-based vectors have been used in clinical trials to deliver therapeutic genes to the striatum or SNpc, showing safety and moderate benefit (Niethammer et al., 2017
Missed Dose Guide What to do if you miss a GLP-1 injection
NPT1/SLC17A1 Is a Renal Urate Exporter in Humans and its Common Gain-Of-Function Variant Decreases the Risk of Renal Underexcretion Gout