We do not know what that means for strength, stability and/or independence
While the underlying mechanisms remain elusive, they are closely associated with mitochondrial adaptation in response to treatments [6,7,8]
By slowing gastric emptying and enhancing satiety, these drugs offer a powerful tool for tackling obesity, a global health crisis affecting over 650 million adults
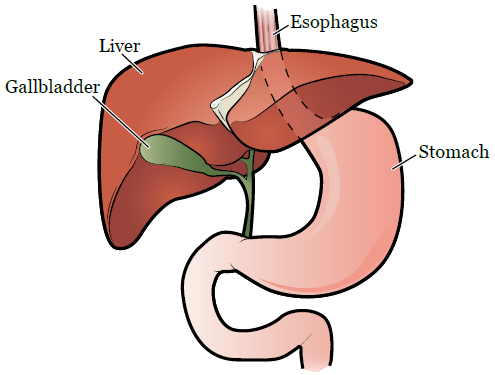
People who have had bariatric surgery Previous bariatric surgery, particularly gastric bypass, permanently alters the digestive anatomy in ways that reduce B12 absorption
Trials are now consistently reporting 1523%: Tirzepatide (SURMOUNT-1): up to 22.5% mean weight loss (72 weeks) Semaglutide dose escalation (STEP UP): 20.7% mean weight loss with 7.2 mg (72 weeks) and ~1 in 3 achieved 25% weight loss 2) Focus is shifting from weight hard outcomes Cardiovascular protection in obesity (no diabetes) SELECT: MACE reduced with semaglutide 2.4 mg 6.5% vs 8.0% events HR 0.80 Kidney + survival benefit in CKD FLOW: semaglutide reduced major kidney outcomes HR 0.76 Also reduced MACE (HR 0.82) and all-cause death (HR 0.80) Sleep apnea is now metabolic SURMOUNT-OSA: tirzepatide improved apnea burden Treatment difference ~20 to 24 AHI events/hour (52 weeks) 3) Biology extends beyond appetite + glucose These therapies influence: inflammation and adipose remodeling vascular and renal pathways cardiometabolic risk clustering 4) Whats next is bigger than GLP-1 alone The pipeline is moving toward: multi-agonists improved pharmacokinetics + oral options precision selection by phenotype expansion into new indications (neuroinflammation, addiction biology, etc.) Clinical takeaway: GLP-1 therapies are transitioning from glycemic agents to disease-modifying cardiometabolic medicines

2025 result report: Calibrate delivers longitudinal real-world outcomes