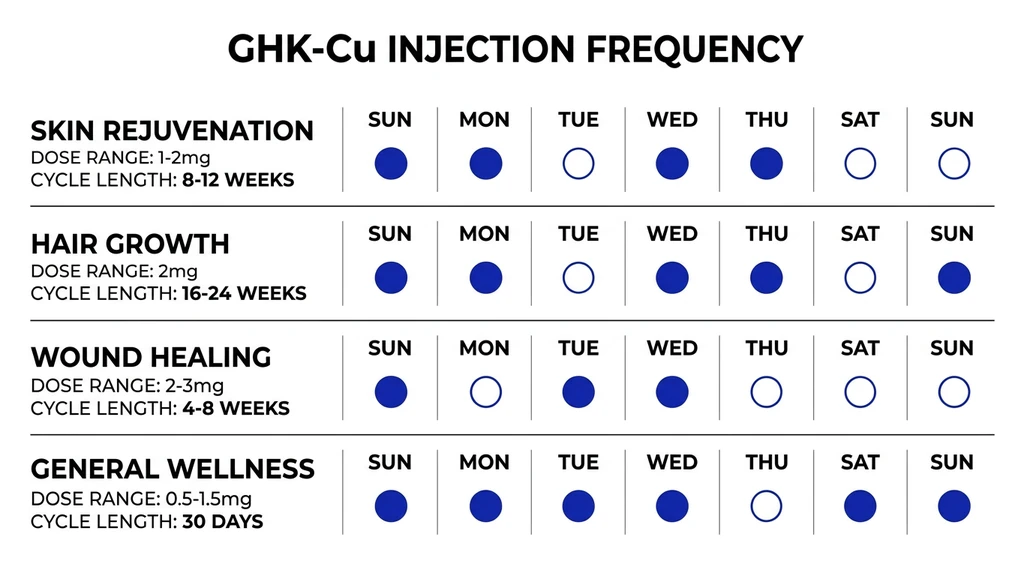
Both regimens fall within the pharmacologically effective range reported in the literature and were administered every 3 days to maintain therapeutic exposure, as described in previous studies (18, 21)
These are powerful pharmacological tools with real side effect profiles, and they're best deployed when the metabolic case for intervention is clear
Patients with kidney problems, especially those with chronic kidney disease, should use semaglutide with caution
In excess, it can even contribute to lean mass loss during a caloric deficit
This convenience factor significantly improves adherence to treatment, which directly impacts results
What I'm seeing with GLP-1s with long COVID may be the first mainstream glimpse of terrain modulation in action