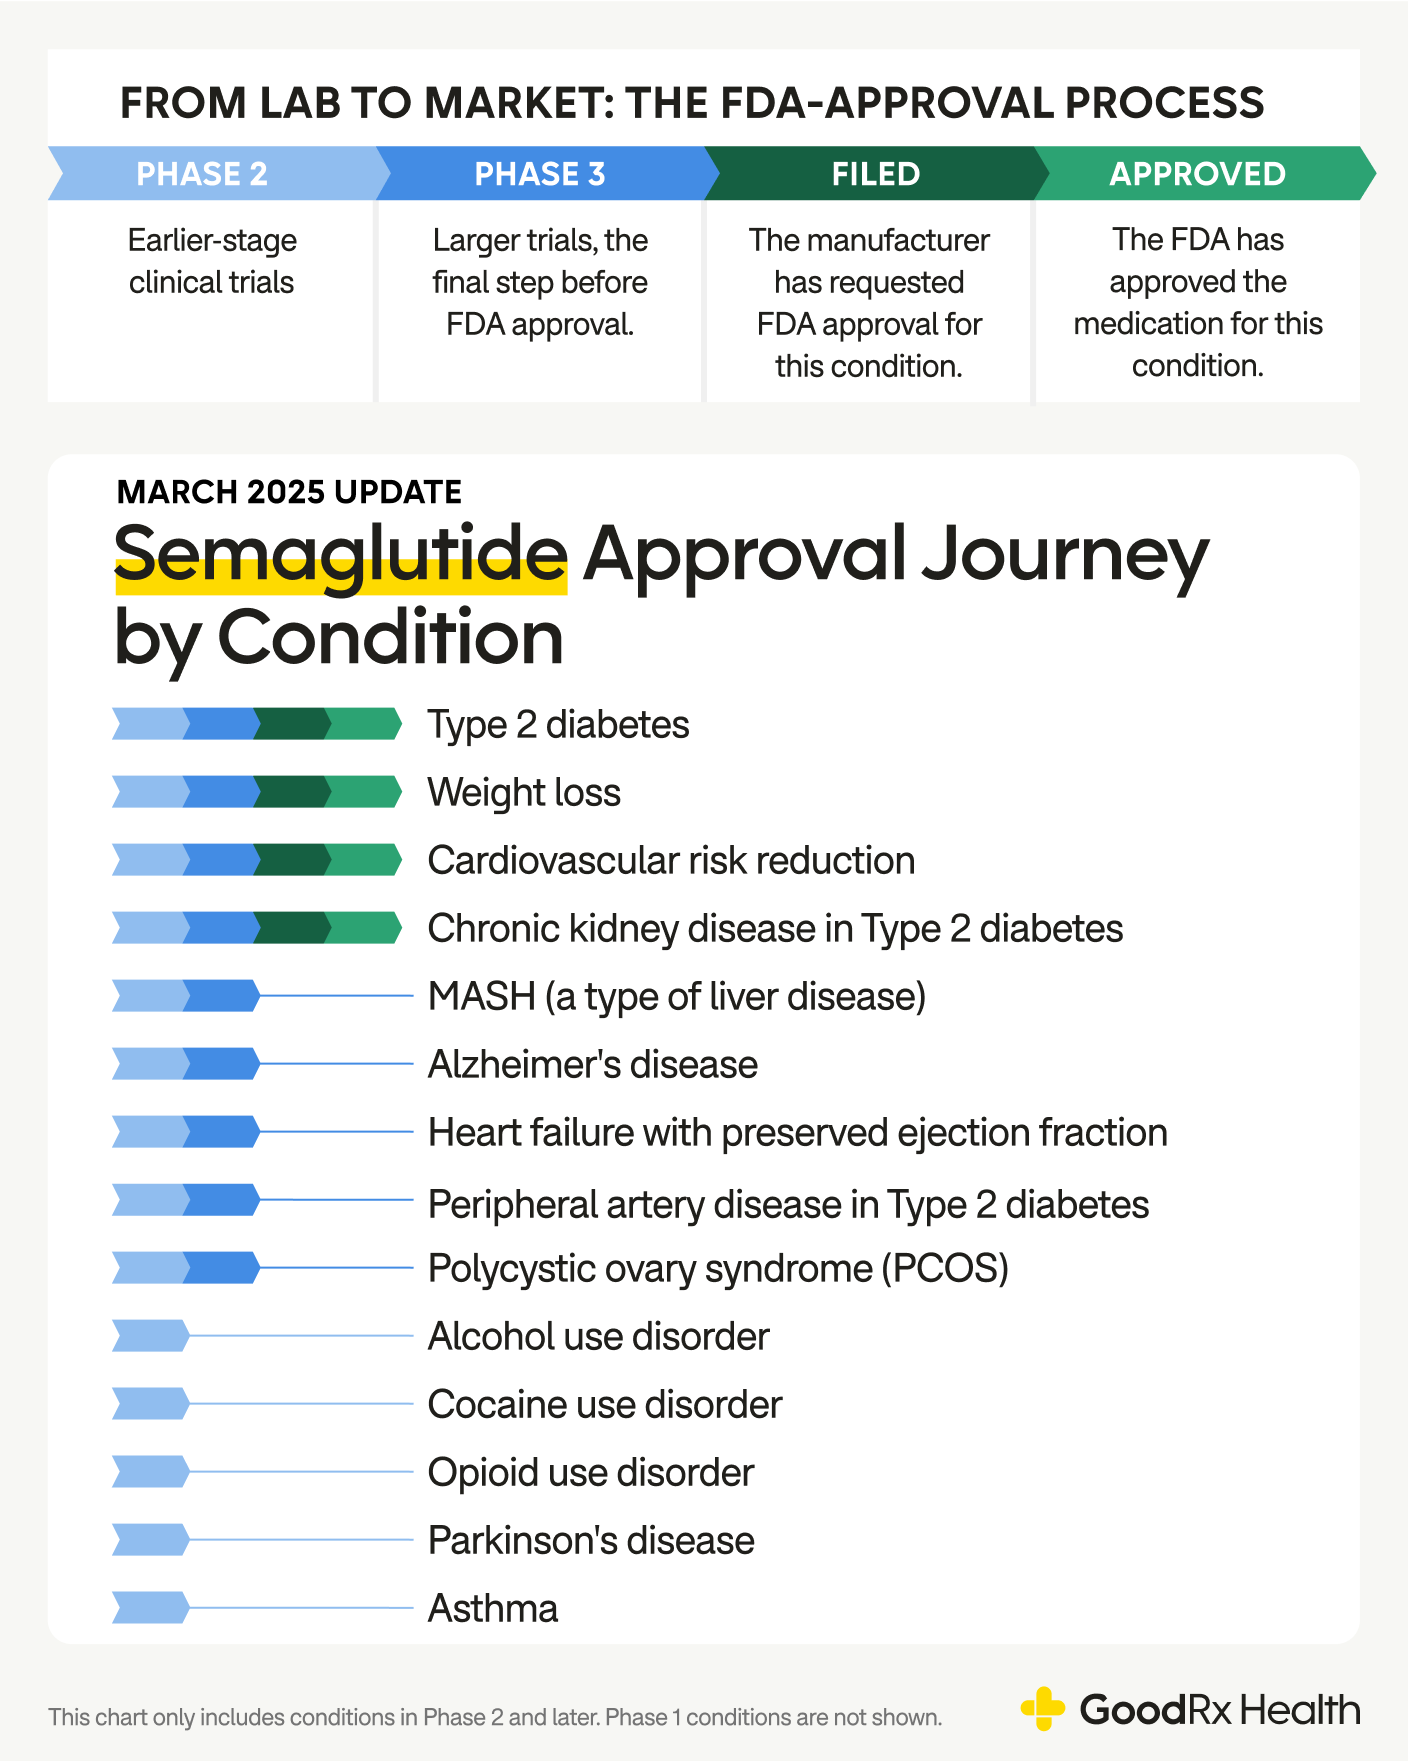
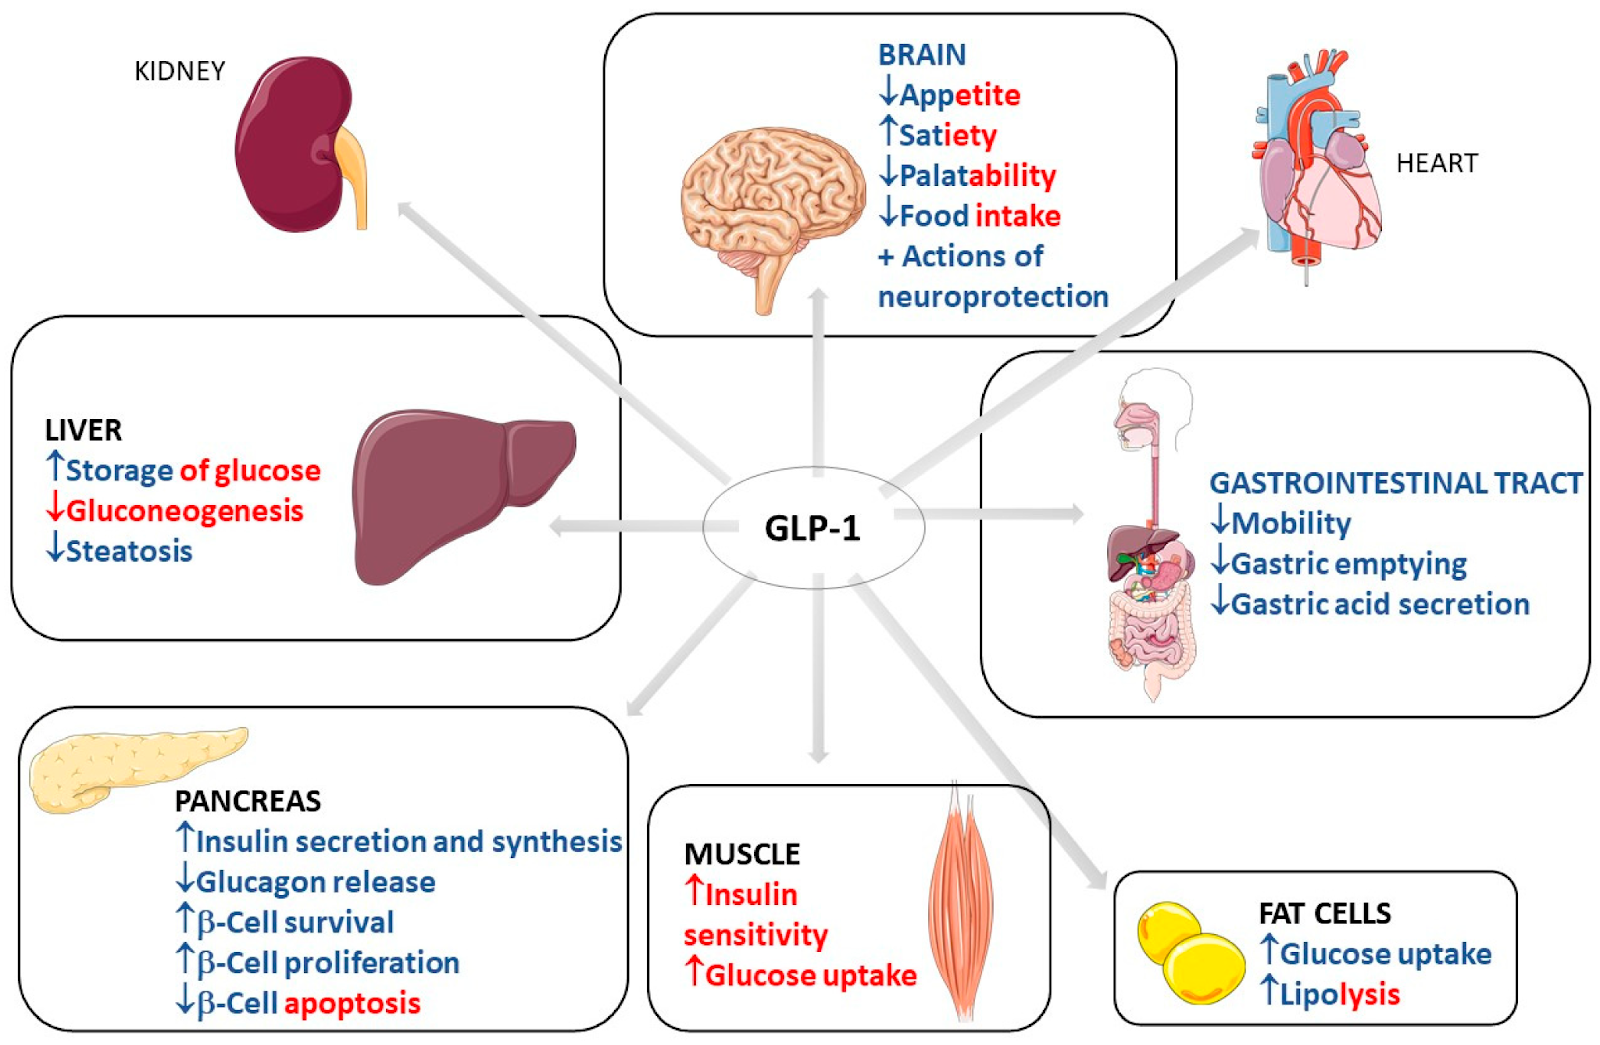
First principles: when stacking makes sense vs when its just noise Heres the simplest clinical lens I know: A stack can be reasonable when it meets all 4 criteria Different primary mechanisms (true complement, not redundancy) A clear problem statement (e.g., Im losing weight but also losing lean mass vs I want to feel optimized) Human evidence exists for at least one component and the combined physiology isnt contradictory You can monitor outcomes and safety objectively (labs, body composition, symptoms, performance, vitals) A stack is usually unjustified when it has any of these patterns Redundant signaling (two compounds tugging the same rope) Unmonitorable goals (recovery, vitality, anti-aging without measurable endpoints) Axis overstimulation (especially GH/IGF-1 signaling) Quality/sterility uncertainty (common with online research vials) No exit plan (no defined stop criteria or reassessment window) The 4 major peptide lanes youll see in stacking culture Most stacks are built from some combination of these buckets: Incretin/metabolic lane (GLP-1/GIP-based pharmacologytypically FDA-approved drugs rather than peptides in the wellness sense) GH/IGF-1 lane (GHRH analogs and ghrelin receptor agonists/secretagogues) Lipolytic fragments/modulators (often marketed for fat loss
Step 2: Choose a bioavailable format
In the case of a glutathione injection, the risks will depend on the dosage and the concentration
The 43-amino acid peptide binds to actin proteins that influence cell shape and movement, promoting tissue regeneration across multiple systems simultaneously
Take back control of your health and your life, and enjoy the body you always wanted.
Fatty liver-mediated glycine restriction impairs glutathione synthesis and causes hypersensitization to acetaminophen